

Polyendocrine metabolic ovarian syndrome (PMOS), long known as polycystic ovary syndrome (PCOS), is a common hormone and metabolic condition. It can affect ovulation, menstrual periods, fertility, androgen levels, insulin response, skin, hair, sleep, mood, and long-term health. The newer name reflects that the condition affects more than the ovaries.
Despite the older name, a person does not need ovarian cysts to have PMOS/PCOS. The “cysts” seen on ultrasound are usually many small, immature egg follicles rather than harmful ovarian cysts. Symptoms and health risks vary, and care should focus on the patient’s goals.
About PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo
Explains the reproductive, hormone, metabolic, and whole-body features of this condition.
Polyendocrine Metabolic Ovarian Syndrome – NIH MedlinePlus
https://medlineplus.gov/ency/article/000369.htm
Explains the updated PMOS name and the condition’s reproductive and metabolic effects.
PMOS/PCOS affects about 10%–13% of reproductive-aged women worldwide. Many people remain undiagnosed because symptoms differ and may be blamed on weight, stress, or normal menstrual changes.
It is one of the most common causes of irregular ovulation and infertility. The condition can affect people at any body size and often continues to influence metabolic health after reproductive years.
Polycystic Ovary Syndrome – World Health Organization
https://www.who.int/news-room/fact-sheets/detail/polycystic-ovary-syndrome
Summarizes symptoms, prevalence, health risks, diagnosis, treatment, and global care needs.
About PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo
Explains the reproductive, hormone, metabolic, and whole-body features of this condition.
Symptoms may begin around the first menstrual periods or develop later. They can include:
Some people have mild signs while others have several. Sudden severe hair growth, deepening voice, or rapidly worsening symptoms need prompt evaluation for another cause.
Symptoms of PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/symptoms
Reviews irregular periods, androgen-related symptoms, fertility concerns, and metabolic effects.
Polycystic Ovary Syndrome – FDA
https://www.fda.gov/consumers/womens-health-topics/polycystic-ovary-syndrome-pcos
Provides current patient information about symptoms, diagnosis, treatment, and medicine safety.
In adults, diagnosis usually requires at least two of three features after other causes are excluded: irregular or absent ovulation; clinical or laboratory evidence of higher androgen activity; or polycystic ovarian appearance on ultrasound. In adults, anti-Müllerian hormone may sometimes support the ovarian feature, but it should not be used as the only test.
If irregular cycles and androgen excess are already present, an ultrasound is not required. Diagnosis in adolescents is more cautious because irregular cycles and acne can be normal early in puberty; both persistent ovulatory problems and androgen excess are generally needed.
Diagnosing PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/diagnose
Explains how history, examination, laboratory testing, and sometimes imaging support diagnosis.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
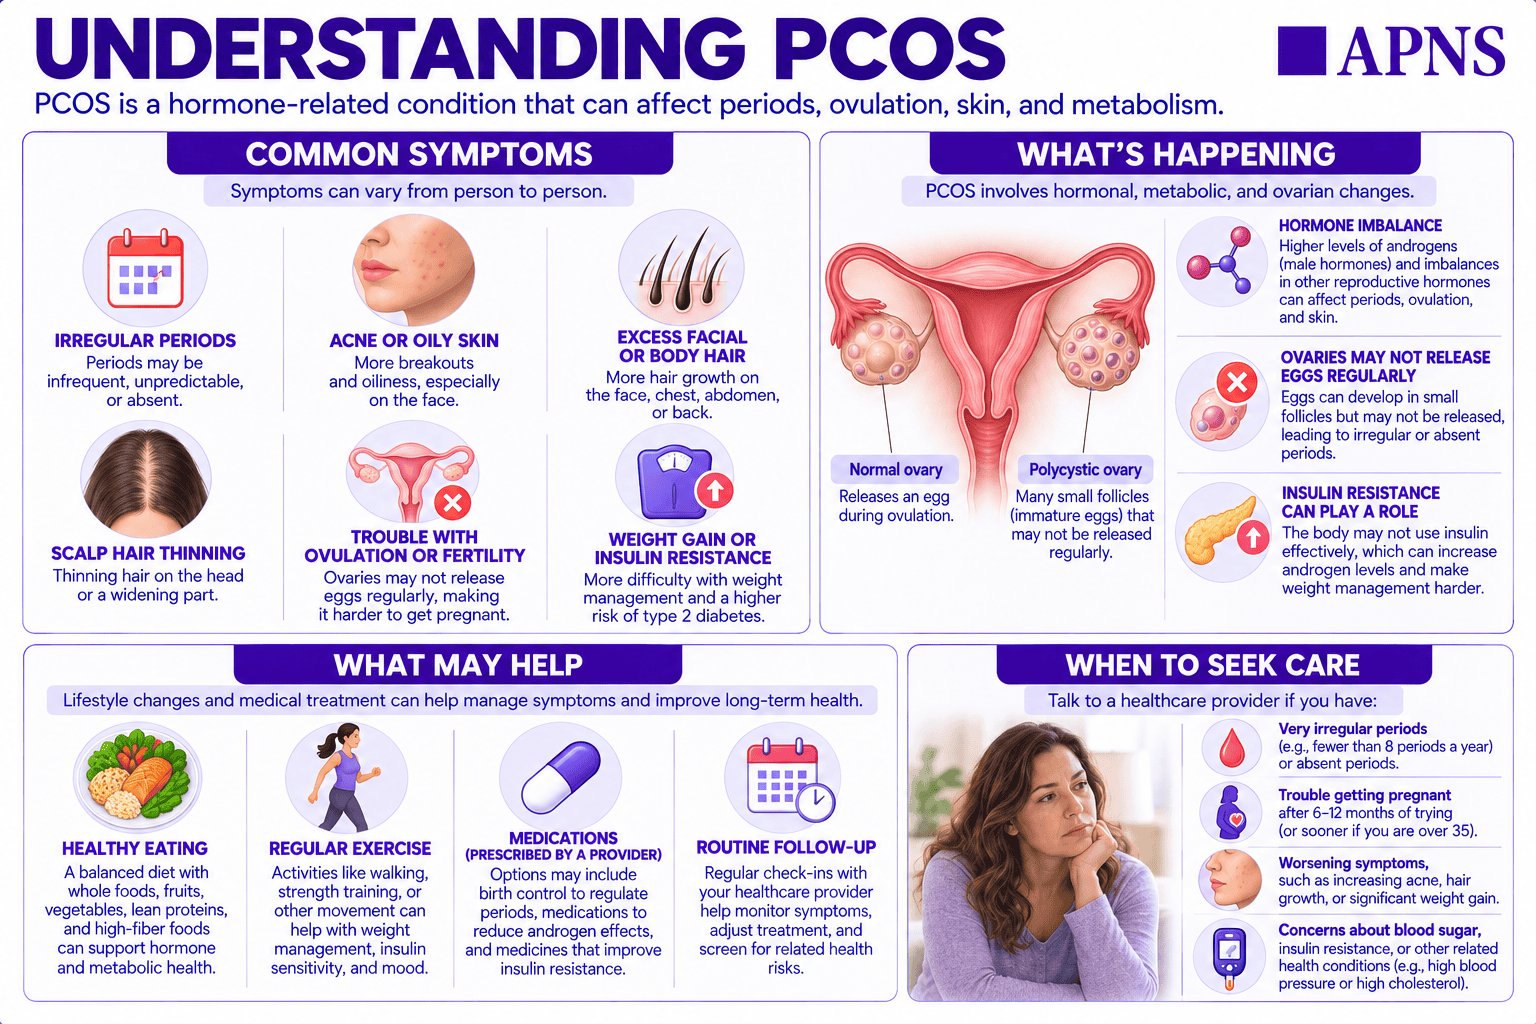
There is no single known cause. Genetics, ovarian and adrenal hormone signaling, insulin resistance, and environmental factors appear to interact.
PMOS/PCOS is not caused by poor hygiene, personal failure, or one food. It can occur in thin, average-weight, or larger-bodied people.
About PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo
Explains the reproductive, hormone, metabolic, and whole-body features of this condition.
Symptoms and long-term risks may worsen with:
Symptoms can change across life stages. Pregnancy, stopping birth control, weight change, stress, and menopause may alter the pattern but do not define the person’s worth or effort.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
PMOS/PCOS cannot always be prevented, but complications can be reduced by:
Care should be free of weight stigma and based on shared decisions. Improvement in health does not require a perfect weight or perfect routine.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Diabetes and PCOS – CDC
https://www.cdc.gov/diabetes/risk-factors/pcos-polycystic-ovary-syndrome.html
Explains the connection between PCOS, insulin resistance, prediabetes, and type 2 diabetes.
The following video content is provided to help you better understand this condition. These resources are intended for educational purposes and should not replace personalized medical advice from your healthcare provider.
Testing helps confirm features, exclude similar conditions, and identify health risks:
Insulin levels are not routinely recommended for diagnosis because available tests are not accurate enough for everyday clinical use. Hormonal birth control can affect androgen results and must be considered when interpreting tests.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Diagnosing PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/diagnose
Explains how history, examination, laboratory testing, and sometimes imaging support diagnosis.
Additional assessment may include:
Routine repeated ovarian ultrasounds are not needed to monitor PMOS/PCOS. Testing should answer a specific clinical question.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Treatment is based on the patient’s priorities, such as predictable bleeding, uterine protection, acne or hair symptoms, metabolic health, pregnancy, contraception, sleep, or emotional well-being.
No single treatment addresses every feature. A plan often combines approaches and changes over time.
Treatments for PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/treatments
Describes lifestyle care, medicines, hair and acne treatment, and individualized symptom management.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Healthy behaviors help metabolic, reproductive, and emotional health at every body size:
There is no single best “PCOS diet.” Benefits can occur without weight loss, and any weight-management goal should be respectful and individualized.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Medicines may include:
No medicine cures PMOS/PCOS. Do not use unregulated “hormone balance” products or supplements without discussing safety, interactions, and pregnancy risk.
Treatments for PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/treatments
Describes lifestyle care, medicines, hair and acne treatment, and individualized symptom management.
Treatments for Infertility Related to PCOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/treatments/infertility
Reviews medicines and procedures that may help ovulation and pregnancy.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Most care does not require a procedure. Options may include:
Removing ovarian cysts is not a routine PMOS/PCOS treatment because the small follicles are part of the hormone pattern, not dangerous cysts that need removal.
Treatments for Infertility Related to PCOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/treatments/infertility
Reviews medicines and procedures that may help ovulation and pregnancy.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
PMOS/PCOS is a long-term condition, but symptoms can be treated and health risks reduced. Period patterns and androgen symptoms may change with age, contraception, pregnancy, and menopause, while metabolic risks can continue.
Follow-up includes blood pressure, glucose status every one to three years based on risk, cholesterol, bleeding pattern, medicines, sleep, and mental health. People with PMOS/PCOS have increased risk of endometrial overgrowth and cancer, but routine screening is not recommended without symptoms; cycle management and evaluation of abnormal bleeding are important.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Diabetes and PCOS – CDC
https://www.cdc.gov/diabetes/risk-factors/pcos-polycystic-ovary-syndrome.html
Explains the connection between PCOS, insulin resistance, prediabetes, and type 2 diabetes.
Helpful self-care includes:
Ovulation can occur unpredictably. Use contraception if pregnancy is not desired, even when periods are irregular.
Yes. PMOS is the newer name used to highlight the condition’s endocrine and metabolic effects; PCOS remains widely recognized.
No. Diagnosis may be made from irregular ovulation and androgen excess after other causes are excluded.
No. The condition occurs at every body size. Weight changes can affect insulin resistance and symptoms but are not the sole cause.
Yes. Many people conceive naturally or with treatment. Irregular periods do not mean pregnancy is impossible.
Long periods without ovulation increase endometrial overgrowth and cancer risk. Overall cancer risk remains low, and regular uterine-lining protection helps.
It may improve ovulation in some people, but letrozole is generally the preferred first-line ovulation-induction treatment when no other infertility factor is present.
No. It manages bleeding and androgen symptoms and protects the uterine lining while it is used.
No, but the risk of abnormal glucose regulation is higher, so periodic testing is recommended regardless of body size.
Consider asking:
Primary care or gynecology can manage many cases. Referral may be made to:
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
There is no permanent cure, but PMOS/PCOS is highly manageable. Treatment can improve periods, protect the uterine lining, reduce acne or unwanted hair, support fertility, and lower diabetes and cardiovascular risk factors.
Symptoms may change over time and may become less noticeable after menopause, but metabolic monitoring remains important. A treatment plan can change as goals change.
About PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo
Explains the reproductive, hormone, metabolic, and whole-body features of this condition.
Polycystic Ovary Syndrome – World Health Organization
https://www.who.int/news-room/fact-sheets/detail/polycystic-ovary-syndrome
Summarizes symptoms, prevalence, health risks, diagnosis, treatment, and global care needs.
Seek urgent or emergency care for:
PMOS/PCOS itself rarely causes an emergency, but pregnancy complications, severe bleeding, ovarian torsion, blood clots, metabolic illness, and mental-health crises require immediate care.
CALL 911
APNS does not provide emergency medical services. If you believe you are experiencing a medical emergency, including (but not limited to) chest pain, difficulty breathing, stroke symptoms, severe allergic reactions, anaphylaxis, uncontrolled bleeding, seizures, loss of consciousness, or any other potentially life-threatening condition, you are instructed to call 911 immediately or go immediately to the nearest emergency department.
About PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo
Explains the reproductive, hormone, metabolic, and whole-body features of this condition.
Symptoms of PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/symptoms
Reviews irregular periods, androgen-related symptoms, fertility concerns, and metabolic effects.
Diagnosing PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/diagnose
Explains how history, examination, laboratory testing, and sometimes imaging support diagnosis.
Treatments for PCOS/PMOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/treatments
Describes lifestyle care, medicines, hair and acne treatment, and individualized symptom management.
Treatments for Infertility Related to PCOS – NIH NICHD
https://www.nichd.nih.gov/health/topics/pcos/conditioninfo/treatments/infertility
Reviews medicines and procedures that may help ovulation and pregnancy.
Polycystic Ovary Syndrome – FDA
https://www.fda.gov/consumers/womens-health-topics/polycystic-ovary-syndrome-pcos
Provides current patient information about symptoms, diagnosis, treatment, and medicine safety.
PCOS – NIH MedlinePlus
https://medlineplus.gov/polycysticovarysyndrome.html
Links to reliable information about symptoms, testing, treatment, fertility, diabetes risk, and genetics.
Polyendocrine Metabolic Ovarian Syndrome – NIH MedlinePlus
https://medlineplus.gov/ency/article/000369.htm
Explains the updated PMOS name and the condition’s reproductive and metabolic effects.
International Evidence-Based PCOS/PMOS Guideline – Monash University
https://www.monash.edu/medicine/mchri/pcos/guideline
Provides international evidence-based recommendations and patient-centered resources for diagnosis and management.
Diabetes and PCOS – CDC
https://www.cdc.gov/diabetes/risk-factors/pcos-polycystic-ovary-syndrome.html
Explains the connection between PCOS, insulin resistance, prediabetes, and type 2 diabetes.
Polycystic Ovary Syndrome – World Health Organization
https://www.who.int/news-room/fact-sheets/detail/polycystic-ovary-syndrome
Summarizes symptoms, prevalence, health risks, diagnosis, treatment, and global care needs.
This guide is for education only and does not replace professional medical advice, examination, diagnosis, or treatment. PMOS/PCOS symptoms overlap with pregnancy, thyroid and pituitary disorders, adrenal conditions, and rare hormone-producing tumors. Seek emergency care for severe bleeding, pregnancy with one-sided pain or fainting, sudden severe pelvic pain, blood-clot or stroke symptoms, severe high blood sugar, or a mental-health crisis. Do not start or stop hormone, metabolic, fertility, or weight-management medicine without clinician guidance.
At APNS, our providers take the time to understand your condition and your goals. We offer comprehensive telehealth visits at a fixed rate — no membership fees, no insurance required, and no unexpected charges. Whether you’re newly diagnosed or looking for a provider who actually listens, we’re here to help.