

Osteopenia means bone mineral density is lower than expected but not low enough to meet the usual DXA definition of osteoporosis. For postmenopausal women and men age 50 or older, a T-score between −1.0 and −2.5 is classified as low bone mass, often called osteopenia.
Osteopenia does not always progress to osteoporosis, and the T-score alone does not determine whether treatment is needed. Age, prior fractures, falls, medicines, medical conditions, and a fracture-risk estimate help show how likely a bone is to break.
Bone Density Scan – NIH MedlinePlus
https://medlineplus.gov/lab-tests/bone-density-scan/
Explains DXA testing, T-scores, preparation, safety, and how results relate to fracture risk.
Bone Mineral Density – NIH MedlinePlus
https://medlineplus.gov/bonedensity.html
Explains low bone density, bone-strengthening habits, and prevention of osteoporosis.
Low bone density becomes more common with age, especially after menopause. Many adults have osteopenia, and because this group is large, many fragility fractures occur in people whose T-scores have not reached the osteoporosis range.
Bone density varies by age, body size, genetics, hormone levels, nutrition, activity, and health history. Screening recommendations differ by age, sex, and risk factors
Osteopenia usually causes no symptoms and does not cause pain by itself. It is often found on a DXA scan or after a low-trauma fracture.
General joint, muscle, or back pain should not automatically be blamed on osteopenia; other causes may need evaluation.
Central dual-energy X-ray absorptiometry, called DXA or DEXA, measures bone density at the hip and spine using very low-dose X-rays. Results are interpreted with age, fracture history, health conditions, medicines, and scan quality.
T-scores are mainly used for postmenopausal women and men age 50 or older. In younger adults, Z-scores compare bone density with people of the same age and sex; a low result should prompt evaluation for an underlying cause rather than simply applying the older-adult label.
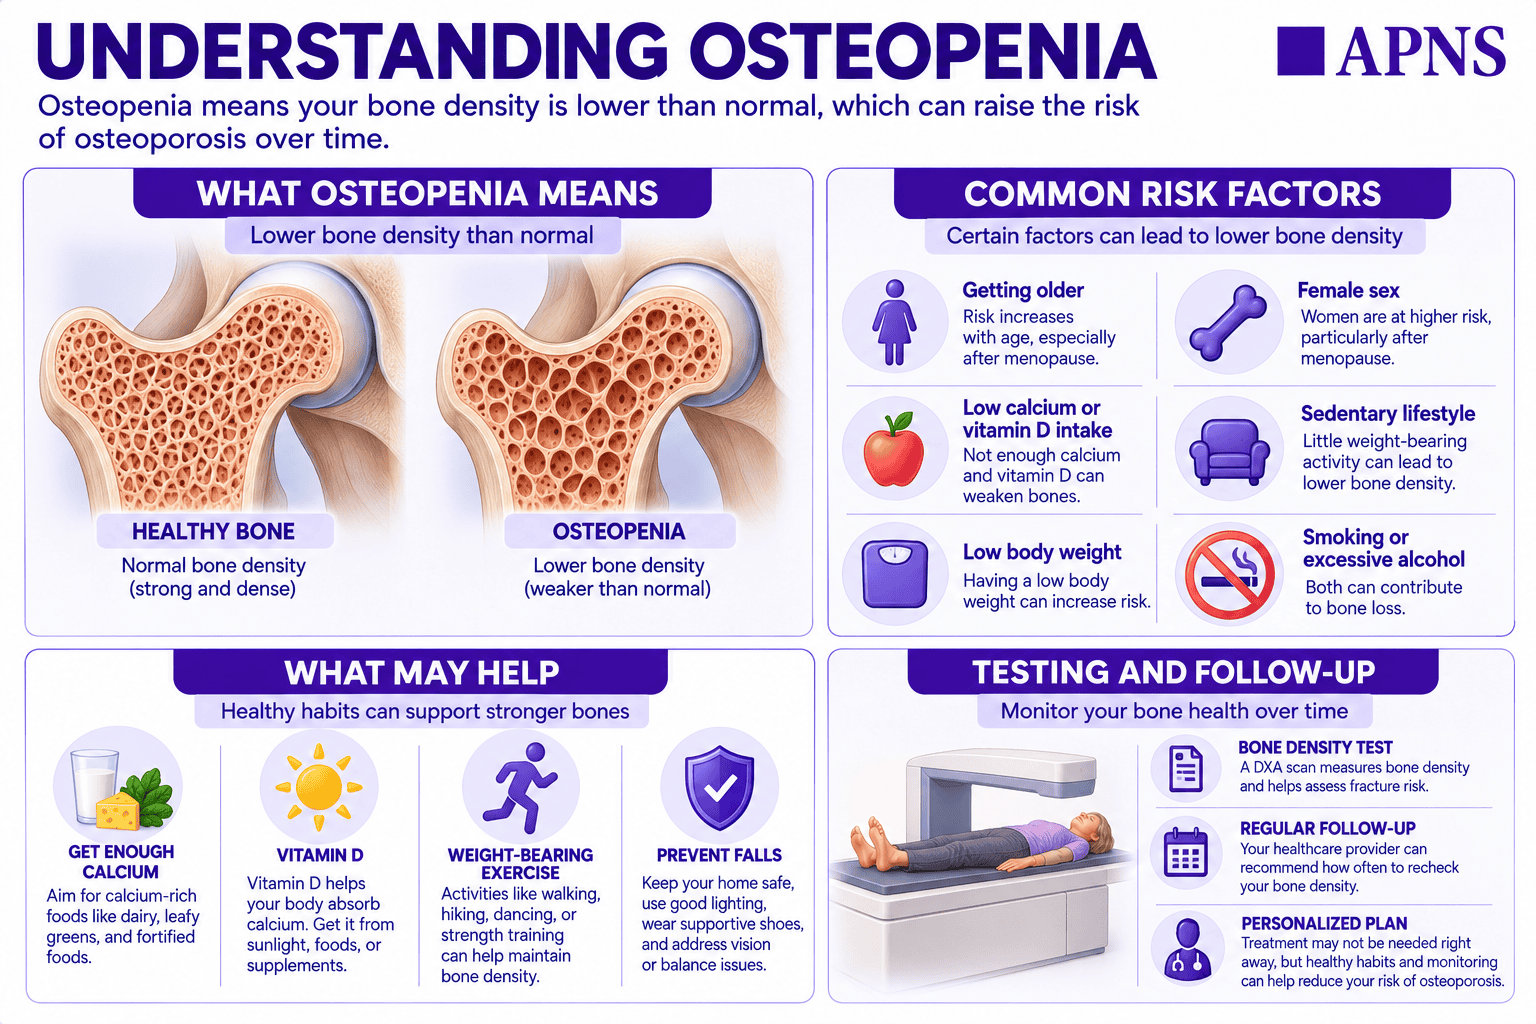
Bone is living tissue that is constantly removed and rebuilt. Osteopenia develops when bone breakdown exceeds bone formation or when peak bone mass was lower earlier in life.
Common contributors include aging, menopause or low sex hormones, low calcium or vitamin D, low body weight, inactivity, smoking, excess alcohol, family history, long-term steroid use, and diseases that affect hormones, kidneys, digestion, blood, or inflammation.
Osteoporosis – NIH National Institute of Arthritis and Musculoskeletal and Skin Diseases
https://www.niams.nih.gov/health-topics/osteoporosis
Reviews bone loss, risk factors, diagnosis, treatment, nutrition, exercise, and fall prevention.
Bone Mineral Density – NIH MedlinePlus
https://medlineplus.gov/bonedensity.html
Explains low bone density, bone-strengthening habits, and prevention of osteoporosis.
The following video content is provided to help you better understand this condition. These resources are intended for educational purposes and should not replace personalized medical advice from your healthcare provider.
Laboratory tests look for reversible causes and help ensure treatment is safe.
Vitamin D Test – NIH MedlinePlus
https://medlineplus.gov/lab-tests/vitamin-d-test/
Explains vitamin D testing, deficiency, supplements, and the role of vitamin D in calcium absorption and bone health.
FRAX estimates the 10-year probability of hip fracture and major osteoporotic fracture in appropriate untreated adults. It combines clinical risk factors and may include femoral-neck bone density.
Spine X-rays or vertebral fracture assessment may find silent compression fractures after height loss, back symptoms, or high risk. A previous hip or vertebral fragility fracture may establish osteoporosis-level risk even when the DXA T-score shows only osteopenia.
FRAX Fracture Risk Assessment Tool – University of Sheffield
Estimates a patient’s 10-year fracture probability using clinical risk factors, with or without femoral-neck bone density.
Everyone with osteopenia benefits from correcting reversible causes, adequate calcium and vitamin D, safe weight-bearing and resistance exercise, fall prevention, and avoiding tobacco and excess alcohol.
Prescription medicine may be recommended after a hip or vertebral fragility fracture, another important low-trauma fracture, or a high FRAX probability. In the United States, commonly used thresholds are at least 3% 10-year hip-fracture risk or at least 20% major-fracture risk, but treatment decisions are individualized.
Exercise, Lifestyle, and Your Bones – NIH MedlinePlus
https://medlineplus.gov/ency/patientinstructions/000492.htm
Provides practical guidance on weight-bearing activity, strength training, balance, smoking, alcohol, calcium, and vitamin D.
Most people with mild osteopenia do not need prescription bone medicine. When fracture risk is high, options may include:
Medicines for Osteoporosis – NIH MedlinePlus
https://medlineplus.gov/ency/patientinstructions/000502.htm
Reviews medicines used when fracture risk is high, including benefits, administration, and important risks.
Osteopenia itself does not require surgery. A fracture may need casting, bracing, physical therapy, or orthopedic repair depending on the bone and severity.
Vertebral augmentation procedures are not routine prevention for osteopenia. Treatment focuses on fracture prevention, recovery, and addressing the cause of bone loss.
Bone density may remain stable, improve, or decline. Change is usually slow, and a small difference between scans may reflect normal measurement variation rather than true bone loss.
Repeat DXA timing depends on the initial score, age, treatment, medical conditions, and risk factors. Testing too frequently may not show a meaningful change; a clinician may recommend an interval of several years or earlier monitoring when risk is high.
No. Osteopenia is lower-than-normal bone density that has not reached the usual DXA threshold for osteoporosis, but fracture risk may still be important.
Usually no. Pain may come from a fracture or another muscle, joint, nerve, or spine condition.
No. Progression depends on age, starting density, hormones, illnesses, medicines, nutrition, activity, and treatment.
Not usually. Calcium supports bone health, but exercise, vitamin D, fall prevention, underlying causes, and sometimes medicine also matter.
Swimming is excellent cardiovascular exercise but does not load bones like walking or resistance exercise.
Often yes. Proper resistance training helps bone and muscle, but technique and intensity should be adjusted after fractures or with high risk.
Osteopenia is often manageable and may improve when a reversible cause is corrected or effective treatment is used. Bone density can also remain stable for many years.
A normal follow-up scan does not erase age or fracture history. Long-term bone health still depends on nutrition, activity, fall prevention, and management of health conditions and medicines.
Osteopenia itself is not an emergency. Seek prompt evaluation after a fall, new severe back pain, sudden height loss, or any suspected low-trauma fracture.
Seek urgent or emergency care for:
CALL 911
APNS does not provide emergency medical services. If you believe you are experiencing a medical emergency, including (but not limited to) chest pain, difficulty breathing, stroke symptoms, severe allergic reactions, anaphylaxis, uncontrolled bleeding, seizures, loss of consciousness, or any other potentially life-threatening condition, you are instructed to call 911 immediately or go immediately to the nearest emergency department.
Bone Mineral Density – NIH MedlinePlus
https://medlineplus.gov/bonedensity.html
Explains low bone density, bone-strengthening habits, and prevention of osteoporosis.
Bone Density Scan – NIH MedlinePlus
https://medlineplus.gov/lab-tests/bone-density-scan/
Explains DXA testing, T-scores, preparation, safety, and how results relate to fracture risk.
Osteoporosis – NIH National Institute of Arthritis and Musculoskeletal and Skin Diseases
https://www.niams.nih.gov/health-topics/osteoporosis
Reviews bone loss, risk factors, diagnosis, treatment, nutrition, exercise, and fall prevention.
Exercise, Lifestyle, and Your Bones – NIH MedlinePlus
https://medlineplus.gov/ency/patientinstructions/000492.htm
Provides practical guidance on weight-bearing activity, strength training, balance, smoking, alcohol, calcium, and vitamin D.
Medicines for Osteoporosis – NIH MedlinePlus
https://medlineplus.gov/ency/patientinstructions/000502.htm
Reviews medicines used when fracture risk is high, including benefits, administration, and important risks.
Vitamin D Test – NIH MedlinePlus
https://medlineplus.gov/lab-tests/vitamin-d-test/
Explains vitamin D testing, deficiency, supplements, and the role of vitamin D in calcium absorption and bone health.
FRAX Fracture Risk Assessment Tool – University of Sheffield
Estimates a patient’s 10-year fracture probability using clinical risk factors, with or without femoral-neck bone density.
This guide is intended for educational purposes only and should not replace medical advice, fracture-risk assessment, diagnosis, or treatment from your healthcare provider. A DXA T-score must be interpreted with age, sex, fracture history, scan quality, medical conditions, medicines, falls, and overall risk. Calcium, vitamin D, exercise, and prescription medicines can cause harm when used incorrectly or may be inappropriate with kidney disease, pregnancy, swallowing problems, low blood calcium, dental concerns, or other conditions. Seek urgent care after a serious fall, for suspected fracture, new neurologic symptoms, or severe jaw or thigh pain while using bone medicine.
At APNS, our providers take the time to understand your condition and your goals. We offer comprehensive telehealth visits at a fixed rate — no membership fees, no insurance required, and no unexpected charges. Whether you’re newly diagnosed or looking for a provider who actually listens, we’re here to help.