

Paronychia is redness, swelling, tenderness, or infection in the skin beside or behind a fingernail or toenail. It begins when the protective seal between the nail and skin is damaged, allowing irritants or germs to enter.
Acute paronychia develops over hours or days and may form a pocket of pus. Chronic paronychia lasts longer than six weeks or keeps returning; it is usually driven by moisture and irritant dermatitis, sometimes with yeast or bacteria present. Treatment differs by type.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
Chronic Paronychia – MSD Manual Consumer Version
https://www.msdmanuals.com/home/skin-disorders/nail-disorders/chronic-paronychia
Explains how moisture and irritation damage the nail fold and how chronic paronychia is treated.
Paronychia is a common nail problem. It can affect anyone, but finger infections are especially common after nail biting, hangnails, manicures, or repeated wet work.
Chronic disease is more likely in healthcare, food service, cleaning, dishwashing, beauty, swimming, and other work that repeatedly exposes hands to water, chemicals, or gloves.
Clear grouped blisters, burning, or tingling may suggest herpetic whitlow rather than bacterial paronychia. Severe deep fingertip-pad pain may indicate a felon, a deeper infection requiring urgent care.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
A clinician usually diagnoses paronychia by examining the nail fold and asking about onset, pain, drainage, injury, nail care, work exposures, biting, water contact, diabetes, circulation, immune health, and medicines.
They check whether pus is present and whether infection has spread into the fingertip pad, tendon, joint, bone, or bloodstream. Herpetic whitlow, ingrown nail, nail fungus, contact dermatitis, psoriasis, wart, cyst, and skin cancer may resemble paronychia.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
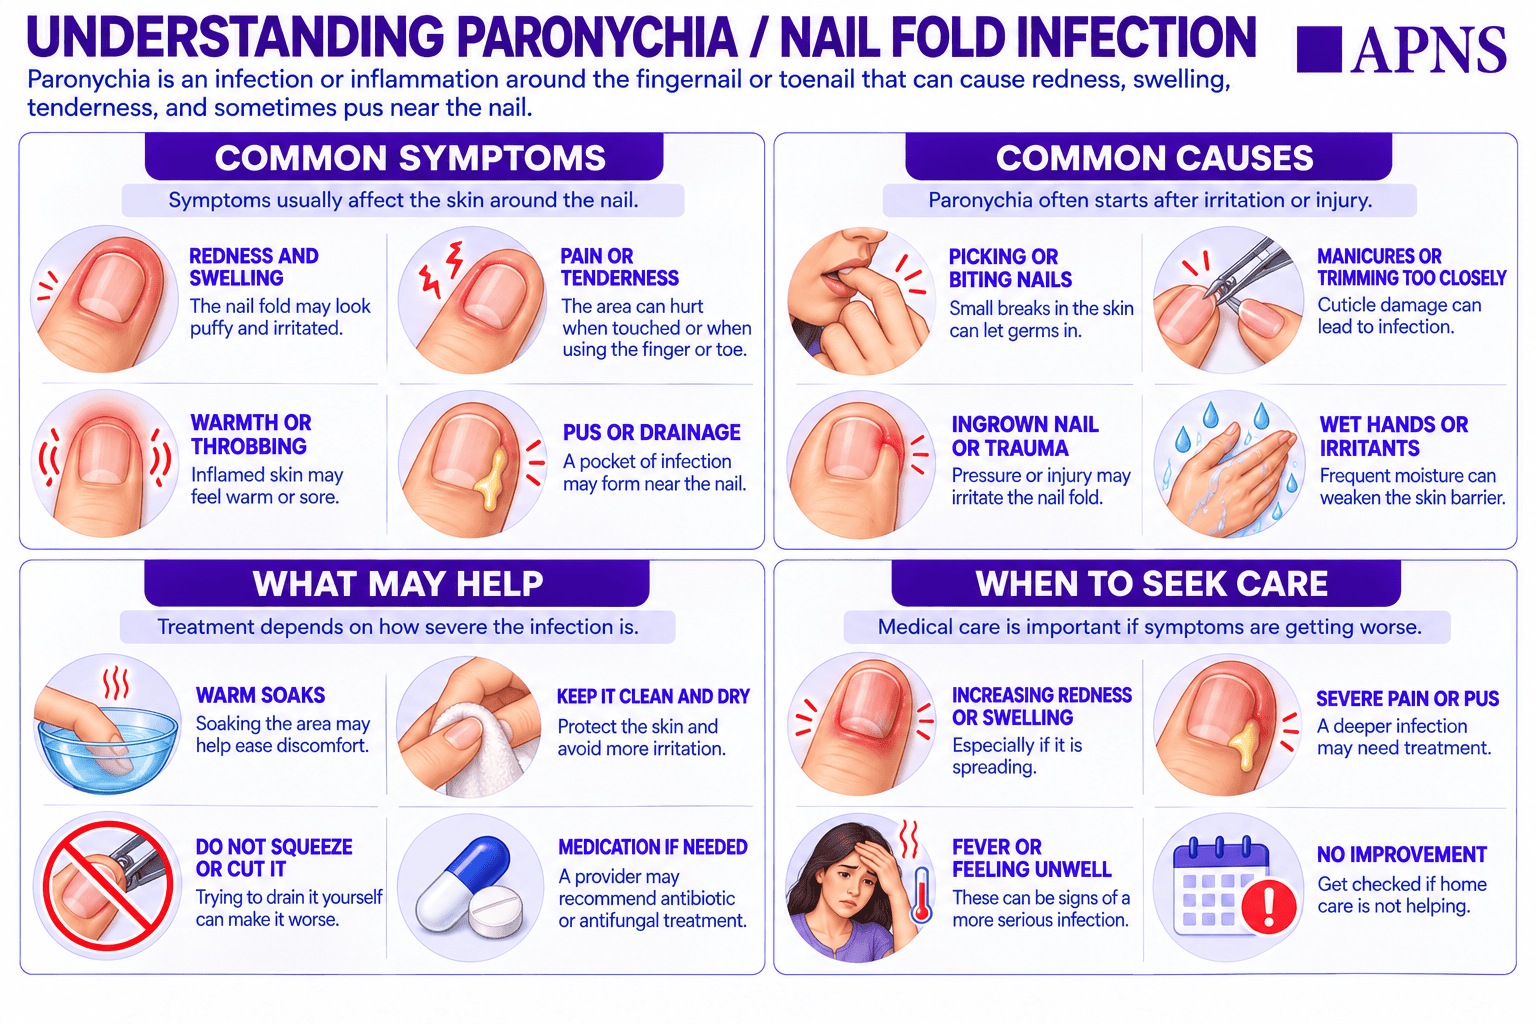
Acute paronychia usually follows a small break in the nail fold. Common bacteria include Staphylococcus and Streptococcus; mouth bacteria may be involved after nail biting or finger sucking.
Chronic paronychia is usually an inflammatory skin-barrier problem rather than a simple fungal infection.
Artificial nails and polish can hide spread or trap moisture. Remove products only if this can be done gently; do not tear or pry an artificial nail from inflamed skin.
The cuticle is a protective seal, not extra skin that must be removed. Preserving it is one of the best ways to prevent paronychia.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
How to Care for an Injured Nail – American Academy of Dermatology
https://www.aad.org/news/how-to-care-for-an-injured-nail
Provides safe cleaning, protection, bandaging, and pain-relief advice for nail injuries.
The following video content is provided to help you better understand this condition. These resources are intended for educational purposes and should not replace personalized medical advice from your healthcare provider.
Routine mild paronychia usually needs no laboratory test. A positive yeast culture does not always mean yeast is the main cause of chronic inflammation.
Fungal Culture Test – NIH MedlinePlus
https://medlineplus.gov/lab-tests/fungal-culture-test/
Describes testing of skin or nail samples when a fungal or yeast infection is suspected.
Do not puncture suspected herpetic whitlow. Opening viral blisters does not help and can spread infection or cause a bacterial infection.
Treatment depends on whether disease is acute or chronic and whether pus, spreading infection, herpes, an ingrown nail, or another condition is present.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
Chronic Paronychia – MSD Manual Consumer Version
https://www.msdmanuals.com/home/skin-disorders/nail-disorders/chronic-paronychia
Explains how moisture and irritation damage the nail fold and how chronic paronychia is treated.
People whose work requires wet hands may need task changes, barrier protection, or occupational-health guidance while the cuticle heals.
Complete prescribed antibiotics and report rash, diarrhea, swelling, or other adverse effects. Topical steroids can worsen some infections if used incorrectly, so confirm the diagnosis first.
A clinician may numb the finger or toe and gently lift the nail fold or make a small opening to drain an abscess. A drain or loose dressing may remain briefly, and part of the nail may be removed when pus extends under it or an ingrown nail contributes.
Do not drain paronychia at home with a needle, blade, nail tool, or heated object. Deep infection may require surgery, IV antibiotics, or removal of a foreign body or damaged tissue.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
Early acute paronychia usually improves within a few days after appropriate treatment. The nail may take months to grow out normally after significant inflammation or injury.
Chronic paronychia often improves slowly because the cuticle needs time to reform. Continued moisture or irritant exposure can cause recurrence, nail ridges, discoloration, separation, or permanent shape changes.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
Chronic Paronychia – MSD Manual Consumer Version
https://www.msdmanuals.com/home/skin-disorders/nail-disorders/chronic-paronychia
Explains how moisture and irritation damage the nail fold and how chronic paronychia is treated.
Do not squeeze, lance, cut, or repeatedly apply peroxide, alcohol, bleach, or essential oils. These can injure tissue and delay healing.
Most bacterial cases do not spread easily through casual contact, but pus can carry germs. Herpetic whitlow is contagious until lesions heal.
No. Home drainage can push infection deeper, damage the nail, or spread germs. A clinician should assess an abscess.
No. Early mild cases may improve with soaks, and a drained abscess may not always require oral antibiotics. Risk and spread determine treatment.
No. It is usually irritant inflammation with a damaged cuticle; yeast can colonize the space but may not be the main cause.
Routine repeated use can irritate healing tissue. Gentle soap and water plus prescribed care is usually safer.
Wait until inflammation and drainage have resolved. Do not allow cuticle cutting, and use clean properly disinfected tools.
Seek prompt evaluation for possible herpetic whitlow. Do not puncture the blisters.
Inflammation may improve quickly, but a damaged fingernail or toenail may take months to grow out.
Most acute paronychia is curable with early care, drainage when needed, and appropriate medicine. Recurrence is less likely when nail-fold injury stops.
Chronic paronychia is usually controllable but may return if moisture and irritant exposure continue. Full nail recovery can take several months because nails grow slowly.
Seek urgent or emergency care for:
Call emergency services for confusion, collapse, breathing trouble, or signs of severe bloodstream infection. Do not wait for a routine visit if infection is spreading quickly.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
CALL 911
APNS does not provide emergency medical services. If you believe you are experiencing a medical emergency, including (but not limited to) chest pain, difficulty breathing, stroke symptoms, severe allergic reactions, anaphylaxis, uncontrolled bleeding, seizures, loss of consciousness, or any other potentially life-threatening condition, you are instructed to call 911 immediately or go immediately to the nearest emergency department.
Paronychia – NIH MedlinePlus
https://medlineplus.gov/ency/article/001444.htm
Explains symptoms, diagnosis, warm soaks, drainage, medicines, complications, and prevention.
Chronic Paronychia – MSD Manual Consumer Version
https://www.msdmanuals.com/home/skin-disorders/nail-disorders/chronic-paronychia
Explains how moisture and irritation damage the nail fold and how chronic paronychia is treated.
How to Care for an Injured Nail – American Academy of Dermatology
https://www.aad.org/news/how-to-care-for-an-injured-nail
Provides safe cleaning, protection, bandaging, and pain-relief advice for nail injuries.
This guide is educational and does not replace professional medical care. Seek urgent evaluation for an abscess, rapidly spreading redness, red streaks, fever, severe fingertip pain, reduced movement or sensation, grouped blisters, or infection with diabetes, poor circulation, or immune suppression. Never cut or drain the nail fold at home.
At APNS, our providers take the time to understand your condition and your goals. We offer comprehensive telehealth visits at a fixed rate — no membership fees, no insurance required, and no unexpected charges. Whether you’re newly diagnosed or looking for a provider who actually listens, we’re here to help.